


New Screening Standards
The American Cancer Society (ACS) issued updated clinical guidelines on November 12, 2026, shifting its approach to prostate cancer detection by recommending regular biennial prostate-specific antigen (PSA) blood testing for the majority of men aged 50 to 69. This move marks a significant departure from previous policies that emphasized flexible, shared decision-making between patients and physicians, reflecting an institutional shift toward standardized screening to address the rising incidence of metastatic disease.
According to the guidelines published in CA: A Cancer Journal for Clinicians, the updated protocol advises annual PSA testing for high-risk groups, specifically Black men and individuals with a strong family history of prostate cancer, starting at age 45. For men aged 70 to 74, the ACS suggests that screening decisions should be individualized based on overall health and life expectancy.
Addressing Rising Mortality Trends
The decision to formalize screening intervals follows a period of concern regarding stagnant or rising mortality rates for advanced-stage prostate cancer. Data from the ACS indicates that diagnoses of metastatic prostate cancer have increased by approximately 6% annually among men aged 55 and older over the past decade. Dr. William L. Dahut, chief scientific officer of the ACS, noted that the organization aims to increase screening uptake among average-risk populations to curb the prevalence of advanced disease while balancing the risks associated with potential overdiagnosis.
Historically, the clinical utility of the PSA test has been debated due to risks of false positives and the potential for overtreating slow-growing cancers that might never cause clinical symptoms. In 2012, the U.S. Preventive Services Task Force advised against routine screening, a period that researchers now correlate with a subsequent creep in late-stage diagnoses. However, recent long-term studies from Europe have provided more robust evidence that consistent screening in middle-aged men can effectively lower mortality, prompting this policy correction.
Clinical Implications and Patient Risks
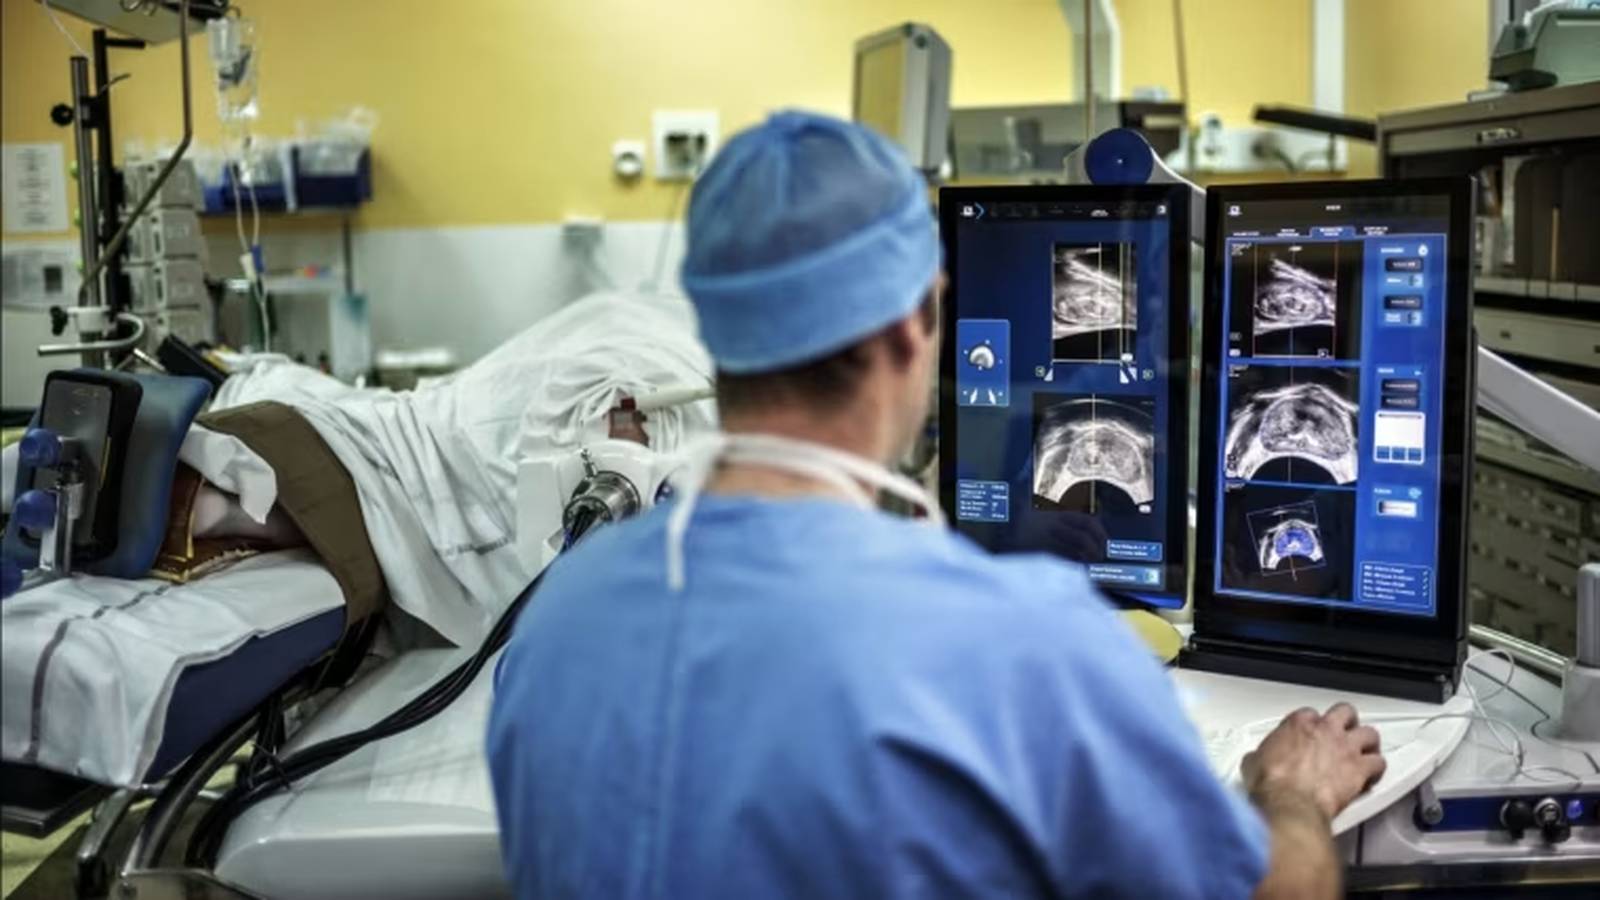
While the PSA test remains the primary tool for early detection, the ACS acknowledges that it is not without drawbacks. The biopsy procedures required for diagnosis carry physical risks, and treatments such as surgery or radiation can result in long-term side effects, including sexual dysfunction and urinary incontinence. The current guidance emphasizes that clinicians must now more actively recommend the test, moving away from the previous “shared decision” model that experts believe led to lower testing rates. Modern medical advancements have improved the ability to differentiate between indolent and aggressive cancers, allowing for better management through active surveillance rather than immediate, invasive intervention.